

Magnetic Therapy for Depression, How PEMF, TMS and ECT Compare
Last Updated::
When antidepressants and talking therapy haven’t lifted depression, people start searching for what else exists, and “magnetic therapy for depression” is one of the first phrases they find. The trouble is that three very different things sit under that label. One is a hospital procedure done under anaesthesia, one is an outpatient treatment with decades of trials behind it, and one is a low-intensity technology that is still being tested.
Depression is common. The World Health Organization’s 2026 fact sheet on depression estimates that about 322 million people live with it, and that only about one third of people with depression in high-income countries receive mental health treatment. Knowing which options are proven, and which are still experimental, helps you ask your doctor better questions.
This guide explains what each electromagnetic therapy is, why some depression needs more than first-line treatment, how each therapy works, what the research shows for TMS, ECT and PEMF, how they compare in practice, and where the evidence still falls short.
What Electromagnetic Therapy for Depression Means
Electromagnetic therapy for depression is a group of brain stimulation treatments that use electricity, or magnetic fields that create small electrical currents, to change activity in brain circuits linked to mood. The National Institute of Mental Health guide to brain stimulation therapies explains that the electricity can be applied through electrodes on the scalp or induced by magnetic fields applied to the head.
Three approaches come up most often. Electroconvulsive therapy, or ECT, passes a controlled electric current through the brain under general anaesthesia. Repetitive transcranial magnetic stimulation, or rTMS, uses a magnetic coil held against the head. Pulsed electromagnetic field therapy, or PEMF, uses much weaker pulsing magnetic fields and, in depression research, has been delivered through helmets fitted with small coils.
Why Some Depression Needs More Than First Treatments
Medication and psychotherapy work well for many people, but not for everyone. A 2010 trial report in Biological Psychiatry by Martiny and colleagues notes that approximately 30% of patients with depression are resistant to antidepressant drugs. The Larsen 2020 study adds that the chance of a good response to another antidepressant is considerably lower once two or more treatment trials have failed, which is the group usually described as having treatment-resistant depression.
That gap is where brain stimulation fits. The NIMH says brain stimulation therapies are usually used only after other treatments have been tried, and that they should be prescribed and monitored by a health care provider with specific training. In other words, they are added to a treatment plan, not used as a do-it-yourself alternative to one. If stress and sleep are part of the picture too, our guide to men’s mental health and sleep covers the everyday habits that sit alongside medical care.
How Each Therapy Delivers Its Signal
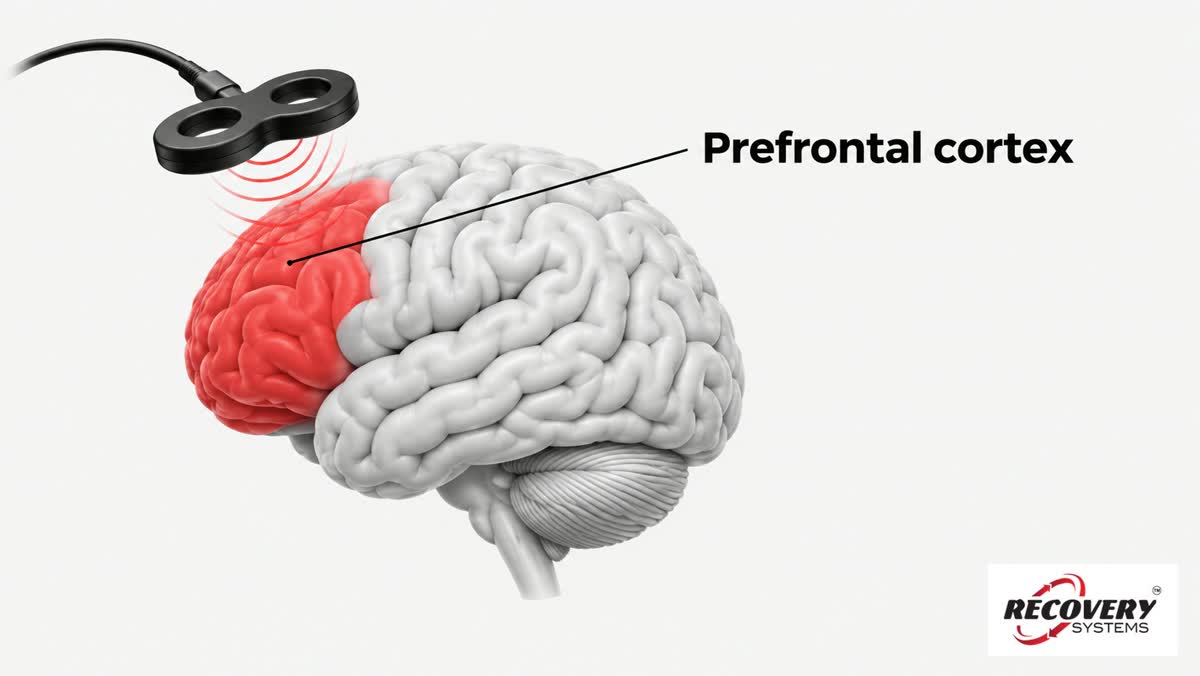
All three therapies aim to change how brain cells fire, but they differ sharply in strength and in how widely they spread. According to the NIMH, the key differences look like this.
- ECT. Electrodes on the head deliver a current that produces seizure activity lasting under a minute, while the patient is asleep under anaesthesia with a muscle relaxant.
- rTMS. A coil held near the left prefrontal cortex switches a magnetic field on and off very rapidly, which induces weak electrical currents in nearby neurons. The field is about the same strength as an MRI scanner, and no anaesthesia is needed.
- PEMF. The helmet used in the Martiny 2010 trial held seven coils and generated an electrical field in tissue that the authors describe as orders of magnitude weaker than rTMS.
So the three sit on a scale. ECT stimulates the brain broadly, rTMS targets one region, and PEMF delivers a far gentler signal whose effects on mood are still being worked out. For the basic physics of pulsed fields, see how PEMF therapy works.
What the Research Shows for TMS
rTMS has the largest body of controlled trials of the three magnetic approaches. A 2014 meta-analysis in Psychological Medicine by Berlim and colleagues pooled 29 randomised, double-blind, sham-controlled trials with 1,371 people with major depression. After about 13 sessions, 29.3% of people on high-frequency rTMS responded and 18.6% reached remission, compared with 10.4% and 5% on sham.
Those numbers are modest but real. The same analysis found drop-out rates were similar between real and sham treatment, which points to good tolerability. The NIMH adds that the FDA cleared the first rTMS device for depression in 2008, has since cleared accelerated protocols, and in March 2024 cleared rTMS as an add-on treatment for adolescents aged 15 and older. NIMH also notes that rTMS does not match the effects of ECT.
What the Research Shows for ECT
ECT has the longest history of use for depression and the strongest effect in severe illness. A 2024 study in the British Journal of Psychiatry by Semple and colleagues analysed ten years of Scottish national data (2009 to 2018) on 2,074 people with moderate to severe depression. It reported a response rate of 73% and a remission rate of 51%.
Response was more likely in older patients and in those with psychotic symptoms, psychomotor slowing or a previous good response to ECT. The NIMH says ECT usually takes effect within the first week, which is why it’s used when someone needs a rapid response, for example when they’re at risk of harming themselves or malnourished.
What the Research Shows for PEMF
PEMF for depression has produced mixed results, and it’s important to see all of them side by side. The early signal was positive. In the Martiny 2010 double-blind, sham-controlled trial, adults with treatment-resistant depression who kept taking their antidepressants used active or sham helmet PEMF for five weeks. The active group did significantly better, with an effect size of 0.62 on the Hamilton depression scale, and side effects were few and mild.
A 2020 Danish multicentre study in European Psychiatry by Larsen and colleagues followed 58 people with treatment-resistant depression through eight weeks of helmet PEMF added to their medication. Average depression scores fell from 20.6 to 12.6, and 49% of those with an episode of two years or less responded. This study had no sham group, so it can’t separate the PEMF effect from placebo or natural recovery.
The most recent controlled data is negative. A 2021 sham-controlled trial in the Journal of Affective Disorders by van Belkum and colleagues randomised 55 people to five weeks of daily active or sham PEMF, with 50 completing. Both groups improved, and active PEMF was not superior to sham on any measure. A 2025 brain scan study from the same Groningen research group found changes in reward-related brain activity after PEMF, but without a clinical antidepressant effect. Sorting real findings from marketing is hard in this field, which is why we wrote a separate piece on common PEMF myths.
How Magnetic Therapies for Depression Compare in Practice
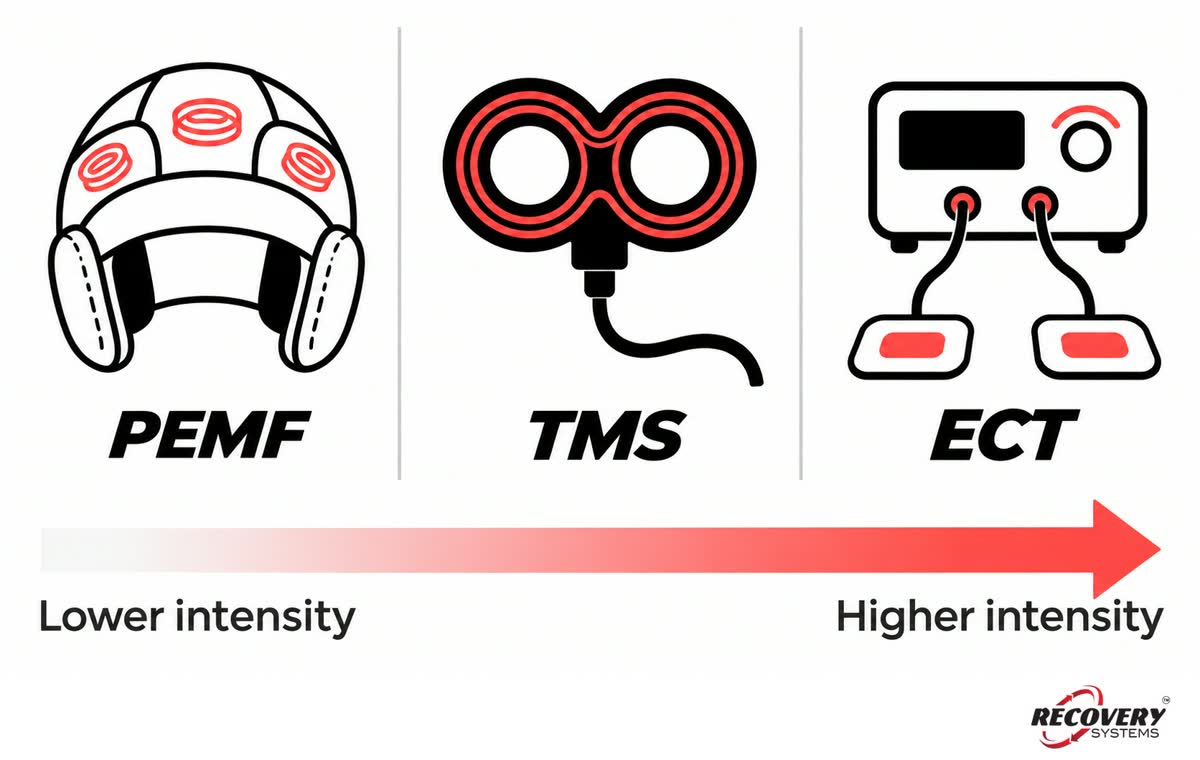
The table below summarises how each therapy is delivered, based on the NIMH overview and the PEMF trials above. It describes what studies and clinics use, not a recommendation for any individual.
| PEMF (research helmets) | rTMS | ECT | |
|---|---|---|---|
| Status for depression | Experimental, not cleared | FDA-cleared | FDA-cleared |
| Anaesthesia | No | No | Yes, general anaesthesia |
| Typical schedule in studies or clinics | 5 to 8 week courses in trials | 5 days a week for 4 to 6 weeks | 3 times a week, usually 6 to 12 treatments |
| Common side effects | Few and mild in trials | Scalp discomfort, headache, lightheadedness | Headache, muscle aches, confusion, memory loss |
| Who delivers it | Research settings | Trained clinic staff | Hospital team with an anaesthetist |
Choosing between them is a clinical decision. Severity, past treatment response, medical history and access all change the answer, so any brain stimulation therapy should be discussed with a psychiatrist. If you’re having thoughts of suicide, call or text 988 in the United States, or your local emergency number elsewhere.
Where the Research Falls Short

Each therapy has its own gaps. For rTMS, the NIMH notes that long-term side effects haven’t been determined. For ECT, memory problems remain the main concern, and NIMH reports they’re more common with older bilateral electrode placement than with unilateral placement and brief-pulse devices.
PEMF has the thinnest evidence of the three. The two most recent studies enrolled 55 people (van Belkum 2021) and 58 people (Larsen 2020, with no sham group), used different field strengths and ran for only five to eight weeks. The van Belkum 2021 authors suggest field strength may explain why their result differed from Martiny’s, and say different dosing regimens weren’t tested. Until larger trials settle that question, PEMF for depression should be viewed as experimental.
It’s also worth being clear about devices. The PEMF studies above used transcranial helmets in research settings. Full-body PEMF mats, including the ones sold on this website, were not tested in these trials and are not designed or cleared to treat depression. PEMF devices of any kind aren’t suitable for people with pacemakers or other implanted electronic devices, or during pregnancy, so check with a doctor first. Our PEMF safety guide explains what FDA clearance does and doesn’t mean.
Conclusion
Magnetic therapy for depression covers three very different treatments. ECT has the strongest effect for severe and urgent depression, with a 73% response rate in Scottish national data. rTMS offers a well-tolerated outpatient option with consistent benefit over sham in pooled trials, though smaller than ECT. PEMF remains experimental, with one positive sham-controlled trial and a newer one that found no difference.
The honest takeaway is that TMS and ECT belong in a plan made with a psychiatrist, and PEMF for depression isn’t ready to be relied on.
Frequently Asked Questions
What Is TMS for Depression?
TMS for depression is a non-invasive treatment that uses a magnetic coil held against the head to stimulate the left prefrontal cortex, a brain region involved in mood. The NIMH explains that the coil switches a magnetic field on and off rapidly, inducing weak currents in nearby neurons. It needs no anaesthesia and is done in a clinic or office. The FDA cleared the first rTMS device for depression in 2008, for people who hadn’t responded to at least one antidepressant in their current episode.
Can TMS Help With Depression and Anxiety?
TMS is cleared for depression that comes with anxiety. The NIMH lists anxiety with depression among the conditions rTMS is FDA-cleared for, along with treatment-resistant depression, obsessive-compulsive disorder, migraine and smoking dependence. Since 2008, rTMS has been cleared for several types of depression, including depression with comorbid anxiety. Anxiety without depression is a different question, and anyone considering TMS for anxiety should ask their doctor what evidence applies to them. We look at the wider device market in PEMF devices for anxiety.
How Effective Is TMS for Depression?
TMS for depression helps a meaningful minority of people. In a 2014 meta-analysis of 29 sham-controlled trials with 1,371 participants, 29.3% of people on high-frequency rTMS responded and 18.6% reached remission after about 13 sessions. On sham, the figures were 10.4% and 5%. The authors estimated that six people need to be treated for one extra person to respond. Results vary between individuals, and a psychiatrist can judge whether TMS suits someone’s history.
Is ECT or TMS Better for Depression?
ECT has the stronger effect, while TMS is gentler and easier to have. The NIMH calls ECT the gold standard for treatment-resistant depression and says rTMS does not match its therapeutic effects. ECT needs general anaesthesia and can affect memory, while rTMS needs no anaesthesia and has mostly mild side effects. Which is better depends on severity, urgency and past response, so the choice is made with a psychiatrist.
What Is Deep TMS for Depression?
Deep TMS for depression is a form of rTMS that uses a different coil design to reach larger and deeper brain structures. The NIMH explains that in deep TMS, two coils may be used to deliver more stimulation to the target region. Standard rTMS uses a single coil over the left prefrontal cortex. The session format is similar, with no anaesthesia and daily outpatient visits, and the choice of coil is made by the treating clinic based on the person’s diagnosis and history.
Does PEMF Therapy Help Depression?
PEMF therapy for depression has mixed evidence and isn’t cleared as a treatment. A 2010 sham-controlled trial found helmet PEMF added to antidepressants beat sham over five weeks. A 2021 sham-controlled trial of 55 people found no difference between active and sham PEMF. These studies used transcranial helmets, not body mats. PEMF should never replace prescribed treatment, and anyone curious about it should raise it with their psychiatrist.
What Are the Side Effects of TMS?
The side effects of TMS are usually mild and short-lived. According to the NIMH, they include discomfort where the coil sits, tingling or twitching of scalp, jaw or face muscles, mild headaches, brief lightheadedness and dizziness. Seizures are possible but a comprehensive review found the risk is low when expert guidelines are followed. NIMH also notes that long-term side effects haven’t been determined, so more research is needed.
What Is Accelerated TMS?
Accelerated TMS delivers several rTMS sessions in a single day, with short breaks in between, instead of one session a day. According to the NIMH, accelerated protocols often work within a week and show similar effectiveness to standard rTMS while shortening the course. The FDA has cleared a rapid-acting form of rTMS for treatment-resistant depression. Because the schedule is intensive, it’s arranged and monitored by a specialist clinic.
How Many Sessions of TMS Are Needed for Depression?
A standard course of TMS for depression is daily sessions, five days a week, for four to six weeks. The NIMH says each session lasts anywhere from 3 to 40 minutes. Accelerated protocols deliver several sessions in one day with short breaks and often work within a week, and the FDA has cleared a rapid-acting form for treatment-resistant depression. The right schedule is set by the treating clinic.
Is Magnetic Therapy for Depression Safe?
The cleared forms of magnetic therapy for depression are considered safe when delivered by trained teams, but none are free of side effects. The NIMH describes rTMS as safe and well tolerated, with a low seizure risk when guidelines are followed, while ECT can cause headaches, confusion and memory loss. In the Martiny 2010 PEMF trial, side effects were few and mild, but long-term safety data for PEMF in depression is limited.
Can a PEMF Mat Treat Depression at Home?
No, a PEMF mat is not a treatment for depression. The PEMF depression studies, including the Martiny 2010 trial and the van Belkum 2021 trial, used transcranial helmets in supervised research settings, and the results were mixed. Full-body PEMF mats were not tested in these trials and are not cleared for depression. If you’re living with depression, keep following the plan agreed with your doctor, and ask them before adding any device.
What Does ECT Feel Like?
ECT isn’t felt during the procedure because the person is asleep under general anaesthesia. The NIMH explains that patients wake 5 to 10 minutes after it ends, may feel groggy, and are usually alert again within about an hour. Afterwards some people have headaches, an upset stomach, muscle aches, confusion or memory loss, especially for events around the time of treatment. These memory problems usually improve over the following days and weeks.
Can Teenagers Have TMS or ECT?
Both TMS and ECT are cleared for some teenagers, with age limits. The NIMH reports that in March 2024 the FDA cleared rTMS as an add-on treatment for depression in adolescents aged 15 and older, and that ECT is cleared for severe depressive episodes in people aged 13 and older. Any decision about brain stimulation for a young person is made by a child and adolescent psychiatrist, alongside the family and the young person’s existing care.
How Long Do the Effects of ECT Last?
The effects of ECT often need follow-up treatment to last. The NIMH says that although ECT is effective for depressive episodes, antidepressant medication, maintenance ECT or both are usually required to sustain the improvement and reduce the chance of symptoms returning. Maintenance ECT can range from one session a week to one every few months, depending on the person’s needs. The plan after a course is set by the treating psychiatrist.
WRITTEN BY
Michael Lyons
Michael Lyons is a recovery specialist with three decades of tech and Meditech experience and 15,000+ hours in endurance sports coaching. The author is not a licensed physician or medical professional. The health information in this article represents the author’s research and personal perspective, not professional medical advice.
MEDICALLY REVIEWED BY
Ayman Shafique, PharmD
Ayman Shafique is a licensed pharmacist with expertise in pharmacology and medical writing. Her work focuses on reviewing and developing evidence-based health and wellness content, ensuring scientific accuracy, clarity, and alignment with current pharmaceutical research. She specialises in translating complex pharmacological and medical information into accessible, reliable content for public and professional audiences.
Medical Disclaimer
This article is for informational and educational purposes only and should not be considered medical advice. The author is a recovery specialist, not a licensed medical doctor or healthcare provider. Health-related claims discussed in this article are based on emerging research and should not replace professional medical consultation. Individual results may vary. Before using any PEMF therapy device or making health decisions based on this article, please consult a qualified healthcare professional, especially if you have pre-existing medical conditions, a known or suspected blood clot, heart or circulation problems, are pregnant, have implanted medical devices such as pacemakers, or are taking medications.
Commercial Disclosure
This website sells PEMF therapy device products, including the PEMF Bio Mat. The author and company have a commercial interest in promoting these products. Content is written to be as accurate and balanced as possible.
References
Berlim, M. T., van den Eynde, F., Tovar-Perdomo, S., & Daskalakis, Z. J. (2014). Response, remission and drop-out rates following high-frequency repetitive transcranial magnetic stimulation (rTMS) for treating major depression. A systematic review and meta-analysis of randomized, double-blind and sham-controlled trials. Psychological Medicine, 44(2), 225–239. https://doi.org/10.1017/S0033291713000512
Larsen, E. R., Licht, R. W., Nielsen, R. E., Lolk, A., Borck, B., Sørensen, C., Christensen, E. M., Bizik, G., Ravn, J., Martiny, K., Vinberg, M., Jankuviené, O., Jørgensen, P. B., Videbech, P., & Bech, P. (2020). Transcranial pulsed electromagnetic fields for treatment-resistant depression. A multicenter 8-week single-arm cohort study. European Psychiatry, 63(1), e18. https://doi.org/10.1192/j.eurpsy.2020.3
Martiny, K., Lunde, M., & Bech, P. (2010). Transcranial low voltage pulsed electromagnetic fields in patients with treatment-resistant depression. Biological Psychiatry, 68(2), 163–169. https://doi.org/10.1016/j.biopsych.2010.02.017
National Institute of Mental Health. (n.d.). Brain stimulation therapies. Retrieved November 7, 2026, from https://www.nimh.nih.gov/health/topics/brain-stimulation-therapies/brain-stimulation-therapies
Semple, D. M., Suveges, S., & Steele, J. D. (2024). Electroconvulsive therapy response and remission in moderate to severe depressive illness. A decade of national Scottish data. The British Journal of Psychiatry, 225(6), 547–555. https://doi.org/10.1192/bjp.2024.126
van Belkum, S. M., de Boer, M. K., Opmeer, E. M., Kortekaas, R., Mulder, T., Woonings, F., Hoenders, H. J. R., Kamphuis, H., Aleman, A., & Schoevers, R. A. (2021). No antidepressant effects of low intensity transcranial pulsed electromagnetic fields for treatment resistant depression. Journal of Affective Disorders, 294, 679–685. https://doi.org/10.1016/j.jad.2021.07.087
van Belkum, S. M., Opmeer, E. M., Geugies, H., de Boer, M. K., Schoevers, R. A., & Aleman, A. (2025). Change in brain activation after transcranial pulsed electromagnetic fields in treatment-resistant depression. European Archives of Psychiatry and Clinical Neuroscience, 275(4), 1165–1175. https://doi.org/10.1007/s00406-024-01797-w
World Health Organization. (2026, September 11). Depressive disorder (depression). https://www.who.int/news-room/fact-sheets/detail/depression
Originally Published::

Author:
Michael Lyons is a biohacking and recovery specialist with three decades of tech and Meditech experience and 15,000+ hours in endurance sports coaching.


