
PEMF Therapy for Diabetic Neuropathy, What the Research Really Shows
Last Updated::
Burning, tingling or numb feet are often the first sign that diabetes has started to affect the nerves. When the pain keeps people awake at night, it’s natural to look beyond tablets, and PEMF therapy is one of the options that comes up most often in searches for diabetic neuropathy treatment.
The question is whether the research backs it up. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), up to one half of people with diabetes have peripheral neuropathy, so a lot of people are asking it. The honest answer is more mixed than most PEMF marketing suggests.
This guide explains what diabetic neuropathy is, how it’s treated today, what PEMF therapy is, what each controlled trial found, how the studies compare, and where the evidence still falls short.
What Diabetic Neuropathy Is
Diabetic peripheral neuropathy is nerve damage caused by diabetes that usually affects the feet and legs first, and sometimes the hands and arms. The NIDDK explains that, over time, high blood glucose and high levels of blood fats such as triglycerides damage the nerves and the small blood vessels that nourish them.
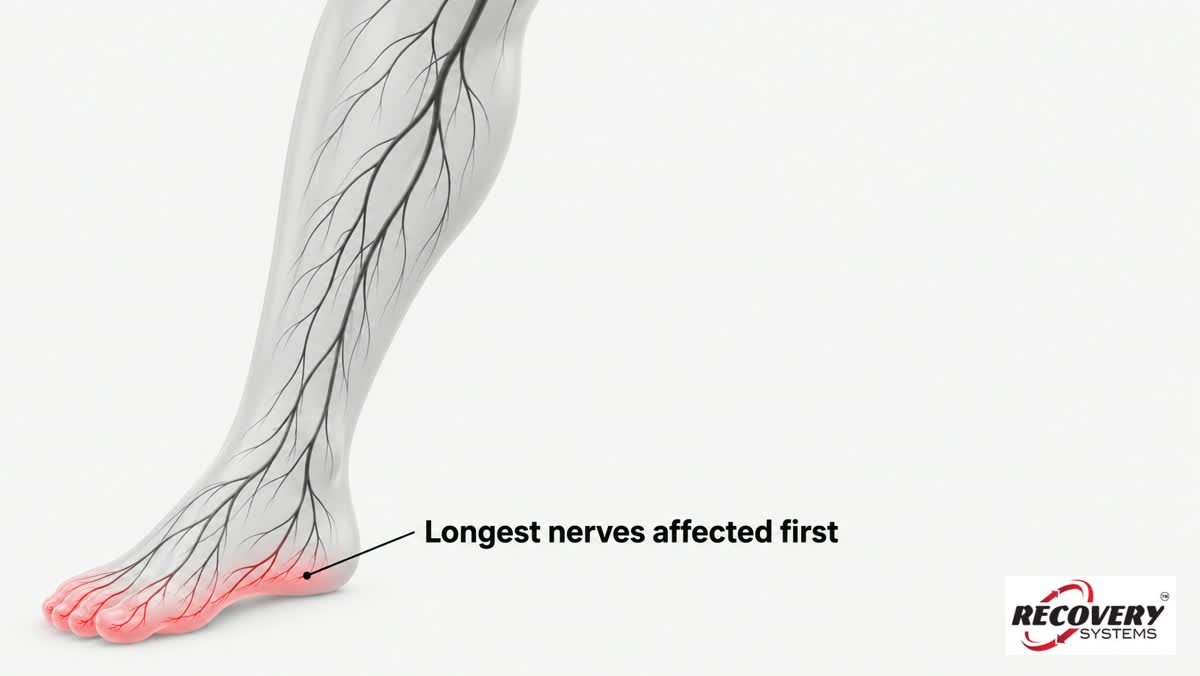
People describe burning, tingling like pins and needles, numbness, pain or weakness. Some feel severe pain even when the skin is touched lightly, while others lose the ability to sense pain or temperature at all. NIDDK notes that symptoms are often worse at night and usually affect both sides of the body.
The numbness matters as much as the pain. When feeling in the feet is reduced, pressure and small injuries go unnoticed, and NIDDK warns that blisters and sores can become infected and, in serious cases, lead to the loss of a toe, foot or part of the leg.
How Diabetic Neuropathy Treatment Works Today
Standard diabetic neuropathy treatment has two jobs, slowing the nerve damage and easing the pain. The NIDDK says that managing blood glucose, blood pressure and cholesterol, and staying close to target numbers, can keep nerve damage from getting worse.
For pain, doctors may prescribe certain antidepressants, such as duloxetine or amitriptyline, anticonvulsants such as gabapentin and pregabalin, or skin creams, patches and sprays such as lidocaine. NIDDK is clear that these medicines can help with pain but don’t change the nerve damage itself, so if one doesn’t help, there’s no benefit in continuing it and another can be tried.
Foot care sits alongside all of this. NIDDK advises checking the feet every day and having a thorough foot exam at least once a year. Physical therapy to improve strength and balance can also help, which links closely to the everyday movement habits covered in our guide to healthy ageing.
What PEMF Therapy Is
Pulsed electromagnetic field therapy, or PEMF, uses a device to produce magnetic fields that switch on and off in pulses. In the diabetic neuropathy trials, these fields were delivered through pads or devices placed on the feet, for anything from 20 minutes to two hours a day. For the basic physics, see how PEMF therapy works.
The idea behind PEMF for nerve pain is that the fields might influence nerve signalling or small blood vessel flow. Those ideas come mostly from laboratory and early clinical work. What matters for anyone with painful feet is whether PEMF reduces pain more than a sham device does, and that’s where the controlled trials come in.
What the Research Shows for PEMF and Diabetic Nerve Pain
Four clinical trials and two recent reviews give the clearest picture. They point in different directions, so it helps to look at each one.
The Largest Trial Found No Pain Benefit
The biggest study is a 2009 randomised, double-blind trial by Weintraub and colleagues in Archives of Physical Medicine and Rehabilitation. It enrolled 225 people with diabetic neuropathy at 16 sites across 13 US states, who used active or sham PEMF devices on their feet for two hours a day for three months.
There were no significant differences in pain intensity between the PEMF and sham groups. More people on PEMF reported overall improvement (44% compared with 31%), and in a small biopsy subgroup of 27 people, 29% of the PEMF group showed an increase in nerve fibre density in the lower leg, compared with none on sham. The authors concluded that PEMF at this dose was not effective for neuropathic pain, while suggesting that higher doses deserved further study.
A Smaller Sham Trial Also Found No Difference
A 2008 double-blind trial by Wróbel and colleagues in Diabetes and Metabolism randomised 61 people with painful diabetic polyneuropathy to a low-frequency magnetic field or sham, 20 minutes a day, five days a week, for three weeks. Pain fell sharply in both groups, from 73 to 33 on a 100 mm scale with real treatment and from 69 to 41 with sham. The difference between groups wasn’t significant at any point, and quality of life, sleep and blood glucose control improved similarly in both.
That large fall in the sham group is a reminder of why sham controls matter. Pain scores can improve a lot during a study even when the device is switched off.
A Company-Funded Trial Reported Less Pain in Some Users
The most positive result comes from a double-blind trial by Tassone and colleagues in the Journal of Diabetes Science and Technology, published online in 2023. It randomised 182 people with painful diabetic neuropathy to active or sham PEMF on their feet, 30 minutes twice a day, for 18 weeks.
People in the active group who never received a low field strength warning, which appeared when the pads were placed incorrectly, reported a 30% reduction in pain compared with sham. Skin blood flow measurements trended towards improvement but didn’t reach significance. Two of the three authors worked for Regenesis Biomedical, a PEMF device company, and the positive result applies to a subgroup rather than everyone randomised, so it needs repeating by independent teams.
Early Studies Without a Sham Group
Smaller early work is often quoted in PEMF marketing. A 2009 study by Graak and colleagues in the International Journal of Diabetes in Developing Countries gave 30 people PEMF at 600 Hz or 800 Hz for 12 days, or usual care. Pain and some nerve conduction measures improved in the PEMF groups. With 10 people per group, a 12-day course and no sham device, it can’t separate the PEMF effect from placebo.
What the Reviews Conclude
A 2026 systematic review and meta-analysis by Lara-Reyes and colleagues pooled 13 sham-controlled trials of PEMF for neuropathic pain, with 688 participants. The overall result looked positive at first, but the studies varied enormously and the effect disappeared after adjusting for missing studies. For peripheral neuropathy specifically, PEMF showed no significant pain reduction.
A 2025 network meta-analysis by Li and colleagues compared neuromodulation treatments for painful diabetic neuropathy across 12 trials and 922 participants. All of them, PEMF included, looked better than sham on pain intensity, but at the final follow-up only spinal cord stimulation showed a statistically significant reduction. If you’re curious how PEMF performs for other kinds of pain, we’ve looked at that in PEMF therapy and chronic pain.
How the PEMF Studies Compare

The table below summarises the clinical trials above. It shows what each study tested, not a recommendation for any individual.
| Study | People | Treatment | Sham group | Pain result |
|---|---|---|---|---|
| Wróbel 2008 | 61 | 20 minutes a day, 5 days a week, 3 weeks | Yes | No difference from sham |
| Weintraub 2009 | 225 | 2 hours a day to the feet, 3 months | Yes | No difference from sham |
| Graak 2009 | 30 | 30 minutes a day, 12 days | No | Improved, no sham to compare |
| Tassone 2023 | 182 | 30 minutes twice a day to the feet, 18 weeks | Yes | 30% less pain in a subgroup |
Put side by side, the two independent sham-controlled trials found no pain benefit, while the one positive sham-controlled trial was company-funded and positive in a subgroup. That’s why PEMF can’t yet be described as an established treatment for diabetic nerve pain. Anyone thinking about trying it should talk to their diabetes team first, and keep up the blood glucose control and foot checks that protect the nerves.
Where the Research Falls Short

The PEMF trials for diabetic neuropathy used different devices, field strengths, session lengths and treatment periods, from three weeks to 18 weeks. That makes it hard to say which settings, if any, help. The Lara-Reyes review describes the evidence as highly fragmented and calls for larger trials designed for specific types of nerve pain.
Some claims also go well beyond the data. Statements that PEMF regrows nerves, restores sensation or reduces the need for pain medication aren’t supported by the sham-controlled trials. The nerve fibre finding in the Weintraub study came from 27 people and was a secondary measure, so it raises a question rather than answering one. Spotting these gaps is a theme of our piece on common PEMF myths.
It’s also worth being clear about devices. The trials above used foot pads and dedicated devices in study settings. Full-body PEMF mats, including the ones sold on this website, were not tested in these trials and are not designed or cleared to treat diabetic neuropathy. PEMF devices of any kind aren’t suitable for people with pacemakers or other implanted electronic devices, or during pregnancy, so check with a doctor first. Our PEMF safety guide explains what FDA clearance does and doesn’t mean.
Conclusion
PEMF therapy for diabetic neuropathy has been tested in several clinical trials, and the results are mixed. The two independent sham-controlled trials, with 61 and 225 people, found no pain benefit over sham. A larger company-funded trial reported 30% less pain in people who used the device correctly, and a 2026 review found no significant effect for peripheral neuropathy overall.
The honest takeaway is that PEMF isn’t an established treatment for diabetic nerve pain. Blood glucose control, daily foot checks and pain medicines chosen with a doctor remain the foundation of care.
Frequently Asked Questions
Can Diabetic Neuropathy Be Reversed?
Diabetic neuropathy usually can’t be reversed, but its progress can often be slowed. The NIDDK says that managing blood glucose, blood pressure and cholesterol, and staying close to target numbers, can keep nerve damage from getting worse. It also notes that pain medicines ease symptoms without changing the nerve damage. The earlier neuropathy is found and managed, the more nerve function there is to protect, so regular foot exams matter.
What Is the Best Treatment for Diabetic Neuropathy in Feet?
The best treatment for diabetic neuropathy in the feet combines blood glucose control, pain relief chosen with a doctor and careful daily foot care. The NIDDK lists certain antidepressants, anticonvulsants and lidocaine creams or patches as pain options, alongside physical therapy for strength and balance. Checking the feet every day and having a foot exam at least once a year help catch sores before they become serious. There’s no single best option for everyone.
Does Gabapentin Help Diabetic Nerve Pain?
Gabapentin is one of the medicines doctors may prescribe for diabetic nerve pain. The NIDDK lists gabapentin and pregabalin, which were originally designed to treat seizures, among the options for neuropathy pain. Like the other pain medicines, it can ease symptoms but doesn’t change the nerve damage. All medicines have side effects, so the choice and dose are set by a doctor or pharmacist who knows your full medical history.
Can You Have Diabetic Nerve Pain Without Diabetes?
Yes, nerve pain that feels the same as diabetic neuropathy can have other causes. When diagnosing peripheral neuropathy, the NIDDK says doctors may run blood tests to rule out thyroid problems, kidney disease or low vitamin B12. That’s why burning or numb feet should always be checked by a doctor rather than assumed to be diabetes. Finding the real cause decides which treatment will help.
What Helps Diabetic Nerve Pain?
Diabetic nerve pain is usually helped by a combination of steady blood glucose control and pain medicines chosen with a doctor. The NIDDK also mentions physical therapy, and a bed cradle that keeps sheets off sore feet at night. It adds that some doctors advise avoiding over-the-counter painkillers such as acetaminophen and ibuprofen, which may not work well for nerve pain and can have side effects.
Can Diabetic Nerve Pain Go Away?
Diabetic nerve pain can ease over time for some people, but it often needs ongoing management. In the Wróbel 2008 trial, pain scores fell substantially in both the treatment and sham groups over a few weeks, which shows how much this pain can change. The NIDDK says that if one pain medicine doesn’t help, another can be tried. Reduced feeling in the feet is a different matter and needs lifelong foot care.
Does PEMF Work for Neuropathy?
The evidence for PEMF in neuropathy is mixed and doesn’t yet show a clear benefit. The largest trial, Weintraub 2009 with 225 people, found no difference in pain between PEMF and sham. A 2026 review of 13 sham-controlled trials found no significant pain reduction for peripheral neuropathy. A company-funded 2023 trial reported less pain in a subgroup. PEMF shouldn’t replace prescribed care.
What Are the Symptoms of Diabetic Nerve Pain in Feet?
The symptoms of diabetic nerve pain in the feet include burning, tingling like pins and needles, numbness, pain and weakness. The NIDDK says some people feel extreme pain from a light touch, while others lose the ability to sense pain or temperature. People may also notice changes in how they walk, loss of balance, swollen feet or pain when walking. Any new symptoms are worth raising at the next appointment.
What Is Diabetic Neuropathy in Feet?
Diabetic neuropathy in the feet is nerve damage caused by diabetes that affects feeling and sometimes strength in the feet. According to the NIDDK, high blood glucose and high blood fats damage the nerves and the small blood vessels that feed them over time. The feet are usually affected first. Because injuries can go unnoticed, it raises the risk of sores and infections.
Is Diabetic Nerve Pain Worse at Night?
Yes, diabetic nerve pain is often worse at night. The NIDDK notes that symptoms of peripheral neuropathy are often worse at night, and suggests a bed cradle to keep sheets and blankets off sensitive feet and legs. Poor sleep can make pain harder to cope with, so night pain is worth mentioning to your doctor. Our article on sleep quality covers general sleep habits.
Can a PEMF Mat Help Diabetic Neuropathy?
No, a PEMF mat is not a treatment for diabetic neuropathy. The trials, including Weintraub 2009 and Tassone 2023, used devices placed on the feet in study settings, and the results were mixed. Full-body PEMF mats were not tested in these trials and are not cleared for diabetic neuropathy. Keep following the plan agreed with your diabetes team, and ask them before adding any device.
Is PEMF Safe for People With Diabetes?
There’s little long-term safety data for PEMF in people with diabetic neuropathy, so caution makes sense. Devices aren’t suitable for people with pacemakers or other implanted electronic devices, or during pregnancy. The NIDDK notes that neuropathy can make it hard to sense temperature, so take extra care with any device that also gives off heat. Speak to your doctor before using PEMF if you have diabetes, especially if you have neuropathy, heart problems or foot wounds.
How Often Should People With Diabetes Have a Foot Exam?
People with diabetes should have a thorough foot exam at least once a year, and more often if they have foot problems. The NIDDK says the exam checks feeling with a tuning fork and a nylon monofilament, and also looks at walking pattern and balance. It suggests taking off socks and shoes in the exam room as a reminder. Checking your own feet every day is just as important.
Do Supplements Help Diabetic Neuropathy?
There’s no official recommendation for supplements in diabetic neuropathy. The NIDDK says diabetes experts haven’t made special recommendations about supplements, and advises talking with a doctor before using supplements or any complementary therapy. One exception is vitamin B12. NIDDK notes that metformin is among the causes of low B12, so a doctor may test for it and recommend a supplement if levels are low.
Is PEMF Approved for Diabetic Neuropathy?
PEMF is not established as a treatment for diabetic neuropathy, and full-body mats aren’t cleared for it. The controlled trials so far have been mixed, with the two independent sham-controlled trials finding no pain benefit. The treatments recommended by the NIDDK are blood glucose control, pain medicines, physical therapy and foot care. Anyone offered a device for nerve pain should ask exactly what it is cleared for.
WRITTEN BY
Michael Lyons
Michael Lyons is a recovery specialist with three decades of tech and Meditech experience and 15,000+ hours in endurance sports coaching. The author is not a licensed physician or medical professional. The health information in this article represents the author’s research and personal perspective, not professional medical advice.
MEDICALLY REVIEWED BY
Ayman Shafique, PharmD
Ayman Shafique is a licensed pharmacist with expertise in pharmacology and medical writing. Her work focuses on reviewing and developing evidence-based health and wellness content, ensuring scientific accuracy, clarity, and alignment with current pharmaceutical research. She specialises in translating complex pharmacological and medical information into accessible, reliable content for public and professional audiences.
Medical Disclaimer
This article is for informational and educational purposes only and should not be considered medical advice. The author is a recovery specialist, not a licensed medical doctor or healthcare provider. Health-related claims discussed in this article are based on emerging research and should not replace professional medical consultation. Individual results may vary. Before using any PEMF therapy device or making health decisions based on this article, please consult a qualified healthcare professional, especially if you have pre-existing medical conditions, a known or suspected blood clot, heart or circulation problems, are pregnant, have implanted medical devices such as pacemakers, or are taking medications.
Commercial Disclosure
This website sells PEMF therapy device products, including the PEMF Bio Mat. The author and company have a commercial interest in promoting these products. Content is written to be as accurate and balanced as possible.
References
Graak, V., Chaudhary, S., Bal, B. S., & Sandhu, J. S. (2009). Evaluation of the efficacy of pulsed electromagnetic field in the management of patients with diabetic polyneuropathy. International Journal of Diabetes in Developing Countries, 29(2), 56–61. https://doi.org/10.4103/0973-3930.53121
Lara-Reyes, J. A., Zarate-Calderon, C., Aranda-Abreu, G. E., García, L. I., & Rojas-Durán, F. (2026). Effectiveness of pulsed electromagnetic field therapy on neuropathic pain. A systematic review and meta-analysis. Neurology International, 18(2), 28. https://doi.org/10.3390/neurolint18020028
Li, L., Luo, X., Liu, Y., Jiang, Y., Chen, Y., Chen, Y., & Wang, J. (2025). Network meta-analysis of randomized controlled trials assessing neuromodulation therapies for painful diabetic neuropathy. Neurology and Therapy, 14(4), 1355–1382. https://doi.org/10.1007/s40120-025-00759-1
National Institute of Diabetes and Digestive and Kidney Diseases. (2018). Peripheral neuropathy. Retrieved November 7, 2026, from https://www.niddk.nih.gov/health-information/diabetes/overview/preventing-problems/nerve-damage-diabetic-neuropathies/peripheral-neuropathy
Tassone, E. E., Page, J. C., & Slepian, M. J. (2025). Assessing the effects of pulsed electromagnetic therapy on painful diabetic distal symmetric peripheral neuropathy. A double-blind randomized controlled trial. Journal of Diabetes Science and Technology, 19(2), 361–369. https://doi.org/10.1177/19322968231190413
Weintraub, M. I., Herrmann, D. N., Smith, A. G., Backonja, M. M., & Cole, S. P. (2009). Pulsed electromagnetic fields to reduce diabetic neuropathic pain and stimulate neuronal repair. A randomized controlled trial. Archives of Physical Medicine and Rehabilitation, 90(7), 1102–1109. https://doi.org/10.1016/j.apmr.2009.01.019
Wróbel, M. P., Szymborska-Kajanek, A., Wystrychowski, G., Biniszkiewicz, T., Sieroń-Stołtny, K., Sieroń, A., Pierzchała, K., Grzeszczak, W., & Strojek, K. (2008). Impact of low frequency pulsed magnetic fields on pain intensity, quality of life and sleep disturbances in patients with painful diabetic polyneuropathy. Diabetes & Metabolism, 34(4), 349–354. https://doi.org/10.1016/j.diabet.2008.02.003
Originally Published::

Author:
Michael Lyons is a biohacking and recovery specialist with three decades of tech and Meditech experience and 15,000+ hours in endurance sports coaching.


